Degenerative Disc Disease: 4 Truths About Why Your MRI May Not Explain Your Pain

Has a diagnosis of "degenerative disc disease" hindered your ability to recover?
80% of adults will experience back pain at some point in their lives. Each year, 30%-50% of the adult population in the US will experience neck pain.
Degenerative Disc Disease is the most common diagnosis for spine pain.

Despite how common it is, the diagnosis of Degenerative Disc Disease is still misunderstood, misleading, and often misdiagnosed.
Degenerative disc disease (DDD) is associated with changes in the intervertebral discs of the spine.
Mislabeling pain as DDD can lead to increased fear, pain, disability, and excessive health care spending on ineffective and risky treatments, AND it can prevent patients from ever finding what is actually driving the pain.
Many myths surround DDD that lead to its misdiagnosis. So, I'd like to share 4 truths about DDD that may make you question if this diagnosis was ever accurate to begin with.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.

Truth #1: The term "disease" is a misnomer.
Many different diseases can cause chronic pain. A few that come to mind are multiple sclerosis, rheumatoid arthritis, Lyme disease, or meningitis.
For the most part, diseases are correlated to a set of distinguishing signs and symptoms. Diseases are usually diagnosed using a well-defined set of diagnostic criteria. DDD has neither of those things.
DDD involves degenerative changes of the intervertebral discs of the spine. But how can we call degenerative changes a "disease" when they are so common in people with and without spine pain?
A 2015 systematic review reported just how common degenerative changes are in individuals without pain.[1] Disc degeneration has a very high prevalence in pain-free individuals ranging from 30% to 96% depending on age group. This study, and many others, demonstrate that these degenerative changes are a normal part of the aging process.[1,2]

This data shows that degenerative changes are not associated with disease, but are a reflection of how we use our bodies over time, like wrinkles on the inside.
So ask yourself, why do we continue to use the term "disease" to describe such a common, age-related adaptation?

Truth #2: No universal set of criteria exists to diagnose DDD.
DDD does not have clear diagnostic criteria. The criteria used to diagnose disc-related problems are ambiguous, inconsistent, and rely on questionable imaging findings.[3] In other words, that diagnosis can be slapped on anything from minimal degenerative changes to extensive damage, even when those degenerative changes may not be the cause of the pain.
Also, DDD can be diagnosed with any anomaly of the disc ranging from mild disc height loss, to cracks in the disc, to severe disc protrusions/extrusions.
Without a clear set of diagnostic criteria, the diagnosis of DDD will continue to be a controversial topic.

Truth #3: Degenerative findings are not correlated to pain.
Individuals with pain have a higher prevalence of some degenerative findings compared to the pain-free population.[2] Yet, these findings still are NOT correlated to pain.[4]
In fact, the only finding that has a strong link between symptoms and MRI findings was severe nerve compression with disc extrusion. Other findings, including mild to moderate nerve compression, disc degeneration, bulging, and central stenosis, are not associated with symptoms.[5]
Studies show how unreliable MRIs are at identifying the exact cause of pain. For example, individuals who were examined before and after developing low back pain had no change on their MRI from their first to their second scan that could explain the onset of their pain. In other words, no differences in the two MRIs could account for the new onset of low back pain.[6]
If you get an MRI, it's very likely that you will have some degenerative findings. Sometimes those findings are pain generators, but many times they are either incidental or only small contributors to the pain problem. DDD may not be the cause of your pain, but that doesn't mean the pain is "all in your head." Lots of other factors can cause or contribute to pain that the MRI can't show: invisible changes in your nerves, muscles, immune system, brain, circulatory system, etc., that diagnostic testing simply can't detect.
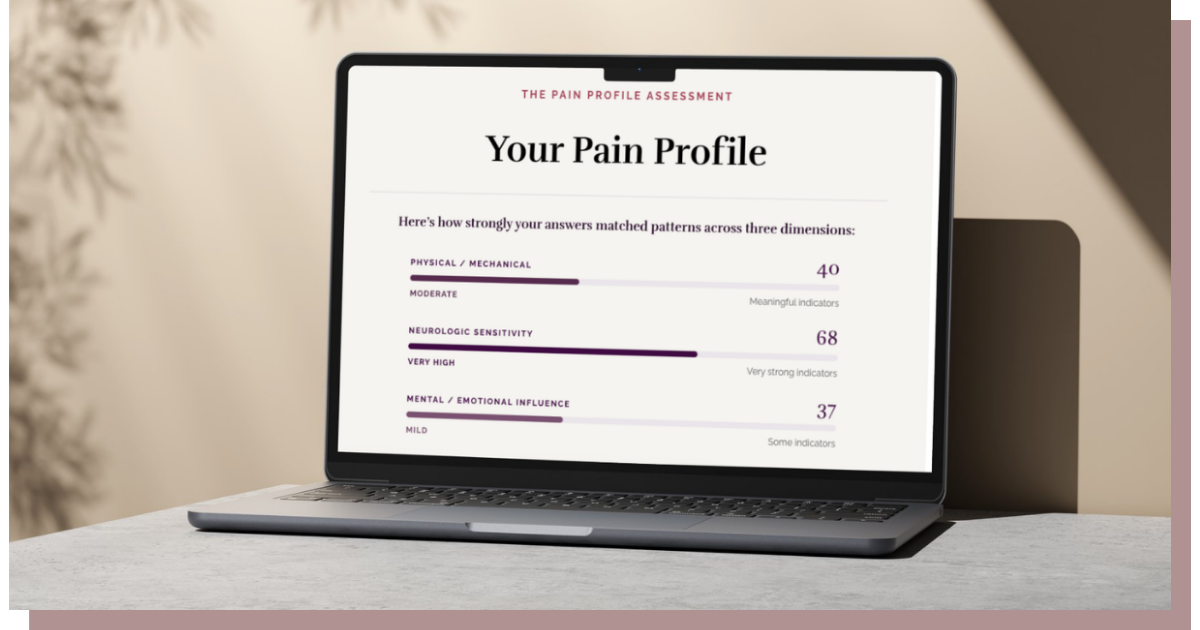
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional. If the neurologic sensitivity score comes back high, the MRI was never going to tell the whole story.

Truth #4: Getting a diagnosis of DDD is not always useful to determine appropriate and effective treatments.
Once degenerative findings are determined as the cause of pain (whether that's true or not), the search for answers slows to a halt. We tend to ignore other possible missed pain generators once a cause of pain is determined. Then, treatments that specifically address DDD are sought after.
Treatments for DDD often involve a progression from least to most invasive procedures. As one treatment fails, you move on to the next, and before you know it, the only options left are invasive procedures or surgery. The success rates for spinal surgery are less than 50% and come with significant risks. 40-60% of people with chronic pain worsen after spinal fusion and up to 27% end up having more than one surgery.
I've had people tell me they don't see how a neuroscience-based approach could help them because they have DDD. They say they've exhausted all their options and there's nothing else they can do. Reaching that point where there's nothing else to do or try for DDD indicates that DDD may be a misdiagnosis. It's very possible that DDD is not the cause of pain, or may not be the only cause of pain.
"There's nothing more we can do" is not an evidence-based statement. It is a statement about the limits of one lens, not the limits of your recovery.
For many, getting a diagnosis of Degenerative Disc Disease is both relieving and absolutely terrifying at the same time. At first, the diagnosis feels like the answer you've been looking for, providing hope and a light at the end of the tunnel.
But then a diagnosis of DDD can quickly become a part of someone's identity. I've seen how it can make people feel unsafe in their own bodies, living with the disabling fear of doing more damage. I've seen how it can lead to an endless cycle of frustration and disappointment with repeated failed treatments that don't live up to their expectations.
The misdiagnosis of DDD leads to more problems and prevents people with persistent pain from ever finding what is actually driving the pain.
This data should make us question the diagnosis of DDD. Is the pain truly caused by those degenerative changes seen on the MRI? Or are those degenerative changes just an incidental finding? Could you have a normally aging spine with pain caused by factors not seen on X-ray or MRI?
Statistically, it's more likely that your persistent pain is related to neurologic sensitivity than to degenerative changes, and while you can have both, the best approach will address those invisible changes that occur in the nervous system.
I designed The Uprising: Complex Pain Academy to teach you more about those hidden nervous system changes that contribute to persistent pain conditions. The program goes in depth into the neuroscience of pain and then addresses pain with techniques that address neurologic sensitivity, along with strategies and skills you keep for life.
Learn more about The Uprising: Complex Pain Academy here, or book a free Pain Care Call to talk it through with me.
References:
- Brinjikji W, Luetmer PH, Comstock B, Bresnahan BW, Chen LE, Deyo RA, Halabi S, Turner JA, Avins AL, James K, Wald JT, Kallmes DF, Jarvik JG. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015 Apr;36(4):811-6. Epub 2014 Nov 27.
- Brinjikji W, Diehn FE, Jarvik JG, Carr CM, Kallmes DF, Murad MH, Luetmer PH. MRI Findings of Disc Degeneration are More Prevalent in Adults with Low Back Pain than in Asymptomatic Controls: A Systematic Review and Meta-Analysis. AJNR Am J Neuroradiol. 2015 Dec;36(12):2394-9.
- Malik KM, Cohen SP, Walega DR, Benzon HT. Diagnostic criteria and treatment of discogenic pain: a systematic review of recent clinical literature. Spine J. 2013 Nov;13(11):1675-89.
- Janardhana AP, Rajagopal, Rao S, Kamath A. Correlation between clinical features and magnetic resonance imaging findings in lumbar disc prolapse. Indian J Orthop. 2010;44(3):263-269.
- Beattie PF, Meyers SP, Stratford P, Millard RW, Hollenberg GM. Associations between patient report of symptoms and anatomic impairment visible on lumbar magnetic resonance imaging. Spine (Phila Pa 1976). 2000 Apr 1;25(7):819-28.
- Savage RA, Whitehouse GH, Roberts N. The relationship between the magnetic resonance imaging appearance of the lumbar spine and low back pain, age and occupation in males. Eur Spine J. 1997;6(2):106-14.